




Why Don't Hospitals Describe the Same Imaging Exam the Same Way?
Hospitals name the same exam differently because each organization builds its own procedure catalog. Medicom research found two institutions describe the same exam with even one identical string only 9% of the time. Those mismatches cause missing priors and repeat scans, so the fix is technology that reads clinical meaning instead of matching exact text.
Share


Table of contents
Ditch the Disc worked, kinda. Fewer patients show up clutching a CD these days, and sending a DICOM from one system to another is now, in the words of Medicom CEO Michael Rosenberg, something "you and I could probably vibe code in a weekend." Getting the system on the other end to understand what it received is where enterprise imaging interoperability breaks down.
Why Is Sending Imaging Easy but Getting It Understood So Hard?
Moving a DICOM file is a solved problem, but the receiving system still has to know which patient it belongs to and what exam it is. That gap was a central theme in Rosenberg's conversation with Jason Nagels on Imaging Informatics Unplugged. It's the root cause of many enterprise imaging failures, and it explains why Ditch the Disc, while well-intentioned, lacked the policy backing to fully succeed.
Why Isn't a Name and Birth Date Enough to Match Imaging to a Patient?
Three data points don't give enough certainty to keep the wrong image out of the wrong chart. Many imaging systems still match patients on a name, a birth date and maybe a medical record number. Rosenberg calls that unsafe, plain and simple. Medicom's approach pulls richer demographics, such as home address, phone and email, straight from the EHR instead of trusting whatever thin data survives in a DICOM header.
Why Do Radiology, Orthopedics and Pathology Name Exams Differently?
Each specialty organizes imaging around its own workflow, so the same study can look different depending on who's asking. A radiologist wants a clean prior to hang next to a new study. Orthopedic surgeons think in terms of what's needed for a specific procedure. Pathology assigns a new accession number to every slide in a case, which looks wrong to a radiologist but makes sense in pathology's workflow.
Rosenberg's answer is an identifier that doesn't depend on naming at all: the Study Instance Unique Identifier (SUID), a code DICOM already assigns to every study. Rather than waiting for two hospitals to agree on a name, the SUID gives each study a fixed identity no matter what either side calls it.
How Often Do Two Hospitals Describe the Same Exam the Same Way?
Only 9% of the time, according to Medicom's research report, Fewer Than 1 in 10 Institutions Describe the Same Exam the Same Way. That's two hospitals performing the exact same exam and sharing even one identical description. A few more numbers worth sitting with:
- Mammography Was the Worst Offender: One of the most routine exams in the country matched between institutions just 3% of the time.
- Six Common Exams, 1,258 Different Names: Basic procedures like a chest X-ray or a pelvic ultrasound turned up under a combined 1,258 distinct descriptions across the network.
- Laterality Gets Dropped Constantly: More than a quarter of descriptions that should specify a side, such as left or right knee, left it out entirely.
- Even the Strictest Field Isn't Safe: Modality is supposed to pull from a short, fixed DICOM list. Real-world data showed 121 different variations.
RadLex, DICOM and FHIR are solid standards, but they get tested inside institutions, where everyone already agrees with themselves. The fragmentation shows up the moment data crosses into another organization's system, which no single IT team can police.
What Do Naming Mismatches Cost Patients, Providers and Health Systems?
Naming mismatches turn routine lookups into repeat orders, and everyone in the care network pays for it.
- Patients: A repeat scan means more radiation, higher costs and delays that have nothing to do with care. It hits hardest for trauma transfers, cancer referrals and anyone whose imaging lives in more than one place.
- Providers: A missing prior usually isn't a missing exam. It's a naming mismatch, and that's the difference between a five-second lookup and a repeat order.
- Health Systems: Your internal catalog looks clean because your staff is consistent. Trouble shows up at the network boundary, where manual compendiums and mapping files were never built to keep up.
Will Policy Make Cross-Network Imaging Exchange a Requirement?
Rosenberg expects it will. Ditch the Disc built real enthusiasm, but without policy backing, organizations faced no penalty for sticking with the old way. With ONC certification requirements likely extending to outpatient radiology and CMS reimbursement rules close behind, cross-network exchange moves from nice-to-have to required. That's the kind of teeth Ditch the Disc never had.
Can Patients Help Close the Imaging Exchange Gap?
Yes, and more than the team expected. Medicom's Patient Upload app lets patients upload imaging from their phones before appointments. Rosenberg said the team doubted anyone would use it. At one New York City health system, patient-uploaded studies have grown to double-digit percentages of total imaging exchange volume, almost entirely from phones rather than desktops or discs.
What Actually Fixes Imaging Naming Mismatches?
Technology that reads clinical meaning instead of matching exact text. Waiting for every hospital to agree on spelling hasn't worked for 20 years, and there's no reason to think it starts working now. Medicom's Smart Search does this today, narrowing an average of 17.3 candidate studies down to the 3.6 that are relevant, so clinicians spend less time sorting and more time on the right image.
The full episode goes deeper, touching on Medicom's expansion into cardiology, why deidentified imaging data isn't as anonymous as safe-harbor rules assume and how automated retrieval works across health systems statewide in Michigan. Watch or listen to Imaging Informatics Unplugged, or schedule a quick walkthrough to see how Smart Search handles the naming and matching problems Rosenberg described.
Frequently Asked Questions
Why do hospitals use different names for the same imaging exam?
Each organization builds its own procedure catalog, and each specialty names exams around its own workflow. Inside one hospital the names stay consistent, but the differences surface as soon as imaging moves to another organization.
How often do two hospitals describe the same exam the same way?
Only 9% of the time, according to Medicom's research. Mammography matched just 3% of the time, and six common exams showed up under 1,258 different names.
What is a Study Instance Unique Identifier (SUID)?
The SUID is a code DICOM already assigns to every imaging study. It gives each study a fixed identity that holds no matter what either hospital calls the exam.
Why do naming mismatches lead to repeat scans?
When a prior exam is named differently at another hospital, clinicians may not find it, so they order the scan again. That adds radiation, cost and delay for the patient.
How does Smart Search help with mismatched exam names?
Smart Search reads clinical meaning instead of matching exact text. It narrows an average of 17.3 candidate studies down to the 3.6 that are relevant, so clinicians find the right prior faster.
More Answers
Answers
How Do You Get Outside Imaging Into the EHR Without a Manual Order?
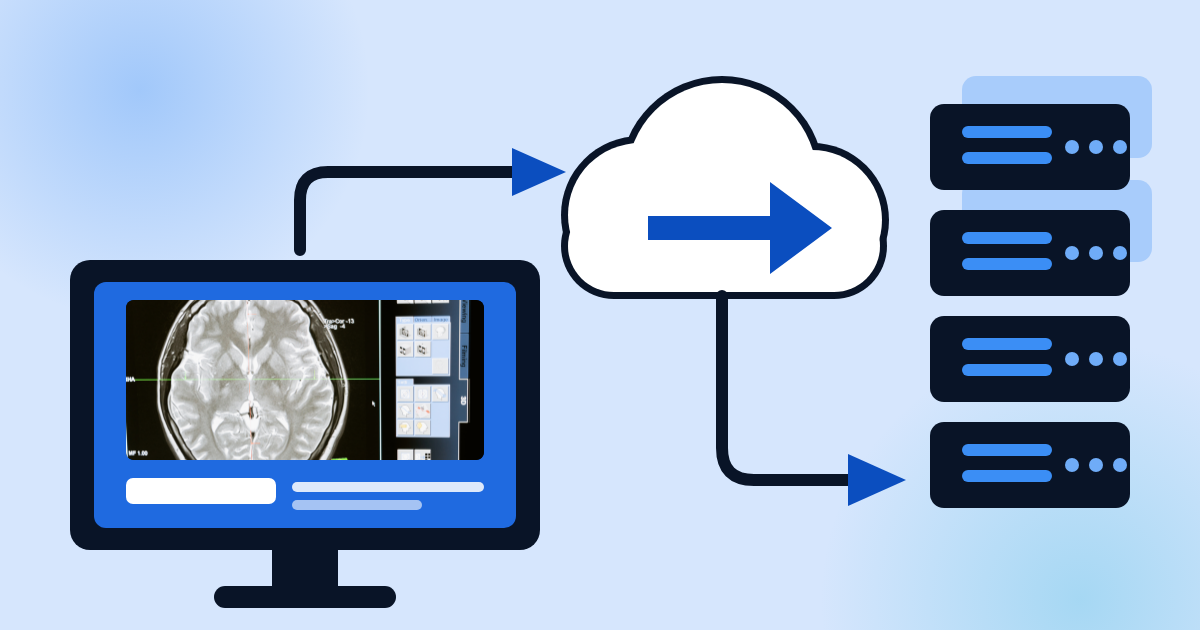
Outside imaging can't attach to the EHR without a matching order and accession number, so it often sits unseen in the archive. Medicom's Auto Order Generation reads the study's DICOM metadata and sends an HL7 order or result automatically, so outside studies show up in the chart just like exams performed on site.
Answers
Why Don't Hospitals Describe the Same Imaging Exam the Same Way?
Hospitals name the same exam differently because each organization builds its own procedure catalog. Medicom research found two institutions describe the same exam with even one identical string only 9% of the time. Those mismatches cause missing priors and repeat scans, so the fix is technology that reads clinical meaning instead of matching exact text.
Answers
What Is Imaging Exchange Analytics, and Why Does It Matter for Your Budget?
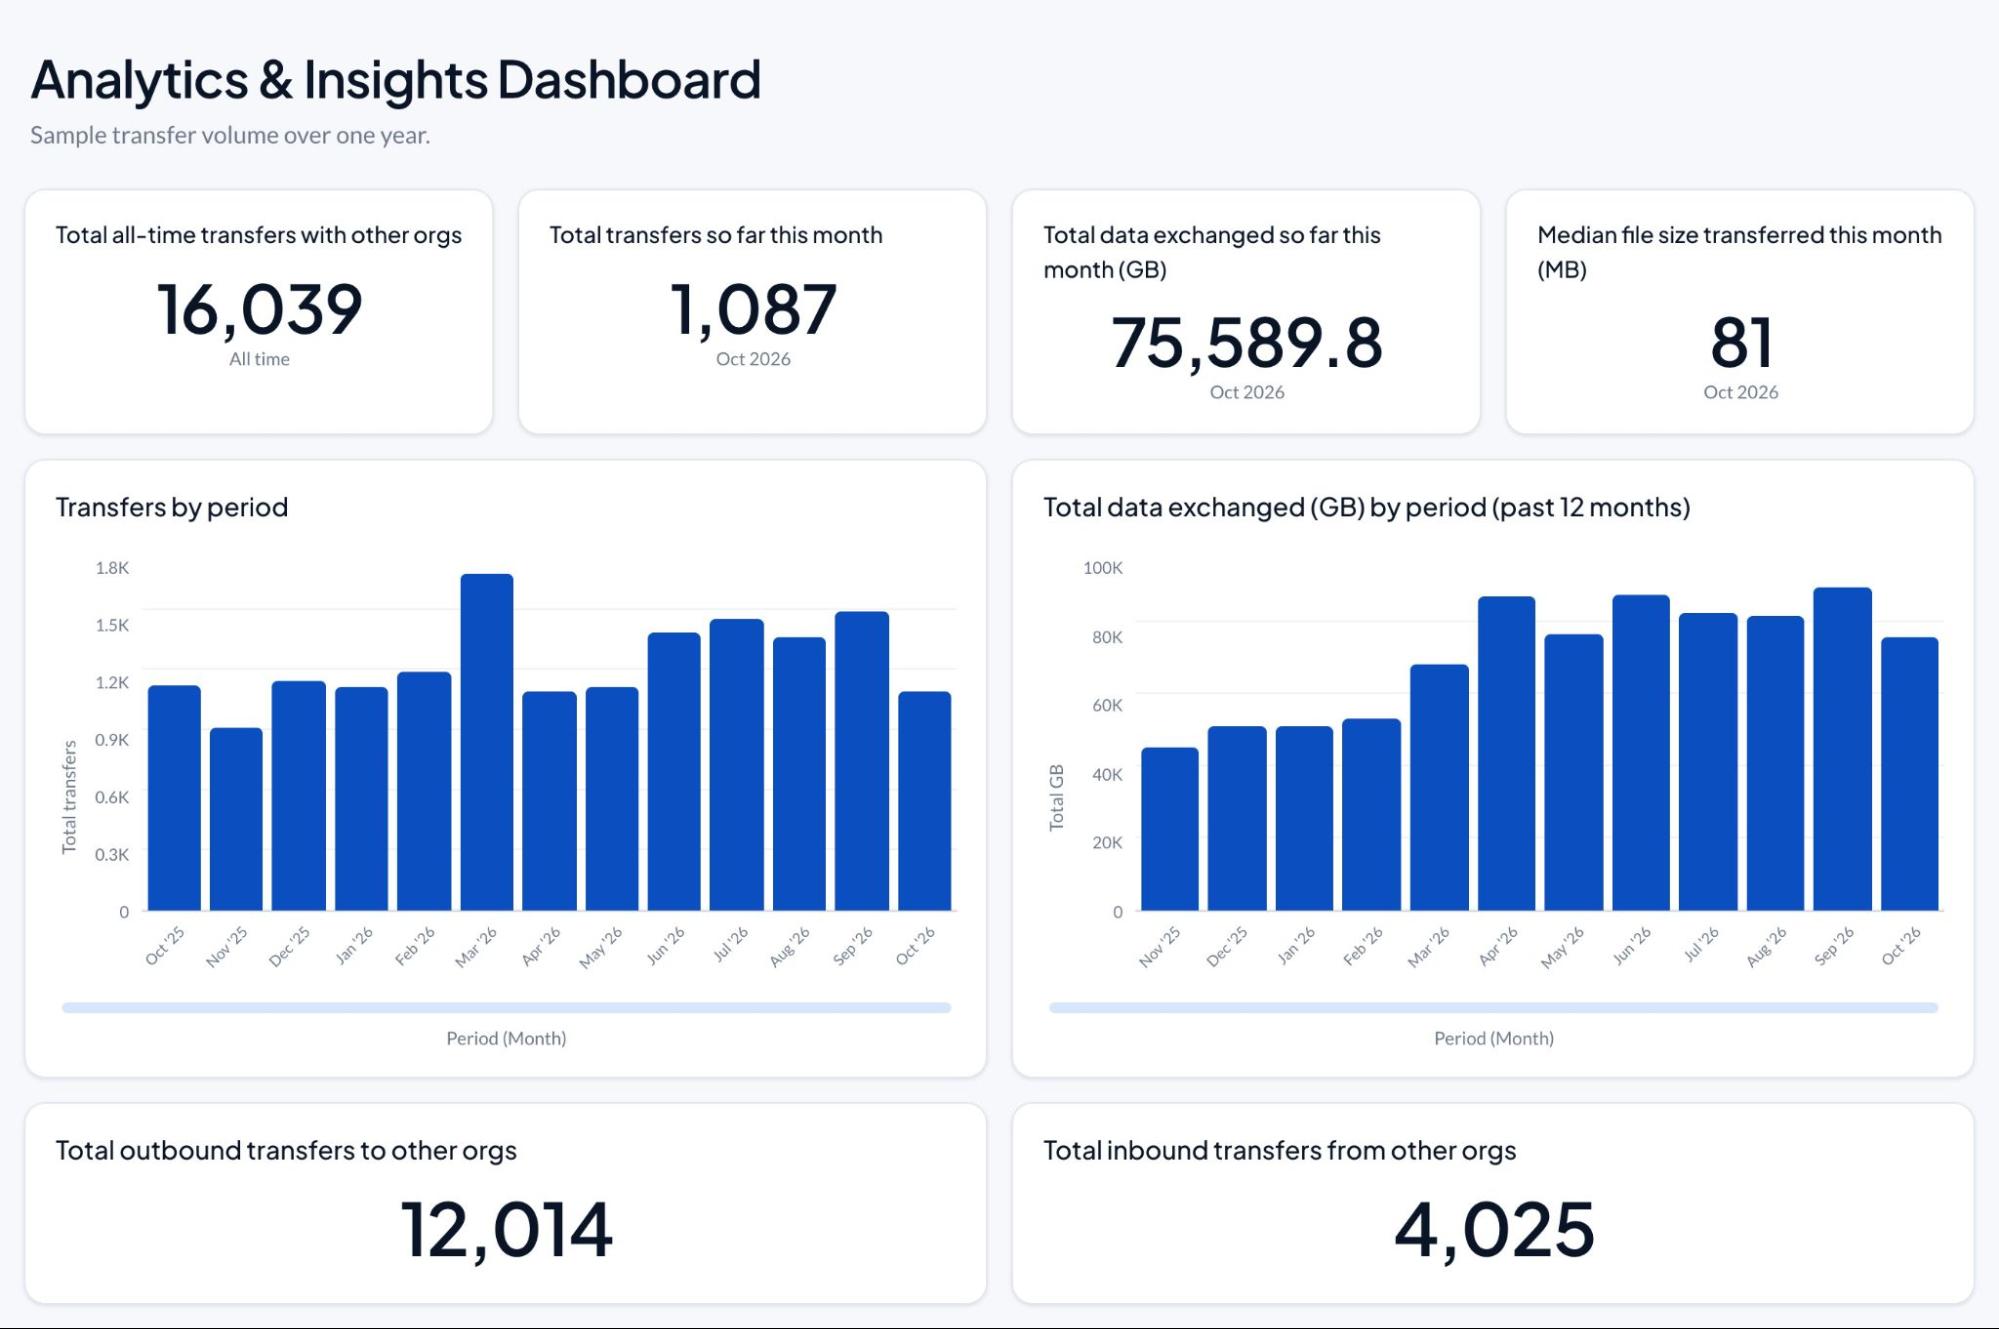
Imaging exchange analytics shows how many studies move in and out of your organization, which partners send them and how your imaging systems are performing. Medicom’s Analytics & Insights gives imaging leaders, exchange managers and IT self-service dashboards for all of it, so budget answers are a click away.
Your Plan for Enterprise Imaging Interoperability
Talk to one of our experts to plan your interoperability strategy, explore workflows, or get a personalized demo. We’re here to help.
